Adolescent Health in the San Joaquin Valley: Individual and Neighborhood Characteristics


Executive Summary





Central California Center for Health and Human Services
1625 East Shaw Avenue, Suite 146Fresno, CA 93710-8106
Phone: 559.228.2150 Fax: 559.228.2168
www.cvhpi.org
Acknowledgement
The San Joaquin Valley Public Health Consortium is a forum for County Public Health Directors, Health Officers, and invited members to explore and exchange ideas and information and to develop strategies for addressing pressing public health issues faced by the counties in the region. The Consortium engages in strategic planning, training, action oriented policy development, and research to improve the quality and responsiveness of public health programs in the San Joaquin Valley region. The vision of the Consortium is to achieve health equity for all residents in the San Joaquin Valley and the mission is to provide leadership for a regional health agenda that addresses the social determinants of health in the San Joaquin Valley. The San Joaquin Valley Public Health Consortium’s core values are to help all residents in the Valley to lead healthy and productive lives through focusing on prevention and by addressing the social determinants of health. The Consortium continually works on building capacity of expert workforce, engaging communities, and utilizing evidence based practice to inform and advocate for health equity in all policies.
This report is the result of collaboration between Consortium members including the eight San Joaquin Valley Counties’ Public Health Departments located in Fresno, Kern, Kings, Madera, Merced, San Joaquin, Stanislaus, and Tulare Counties; Adventist Health Central Valley Network, University of California, Merced, California State University, Fresno and the Central Valley Health Policy Institute at Fresno State. Funding for this publication was made possible by a grant from The California Endowment.
The authors would especially like to thank Amanda Conley, Donna DeRoo, Ashley Hart, Magdalena Flores, Diahann Gutierrez, Jacqueline Cortez, and Yesenia Silva who took the time to edit the report and facilitate the process. You are a gift and we deeply appreciate your work.
We would like to extend a special acknowledgement to Dr. Jody Hironaka-Juteau, David Pomaville, David Luchini, Bill Mitchell, Cathy Volpa, Charles Sandefur, Dr. Claudia Jonah Elizabeth Gazarek, Dr. John Walker, Dr. Karen Furst, Dr. Karen Haught, Kathleen Grassi, Keith Winkler, Dr. Miguel Perez, Dr. Paul Brown, Dr. Steve Roussos, Dr. Tim Livermore, and Van Do Reynoso for providing insights, excellent and extensive advice throughout the project and peer review comments for publication.
Funding and Contributors:
The California Endowment (TCE) and the San Joaquin Valley Public Health Consortium commissioned this project to identify and highlight the social and environmental determinants of health throughout the life course for populations residing in California’s San Joaquin Valley. The Consortium contracted the Central Valley Health Policy Institute (CVHPI) at Fresno State to produce county-specific briefs as well as region-wide reports on the health landscape for the eight local county health departments who participate in the SJVPHC including: Fresno, Kern, Kings, Madera, Merced, San Joaquin, Stanislaus, and Tulare. This document provides analysis of variety of secondary data sources including hospital care use from the Office of Statewide Planning and Development (OSHPD), birth and death records from the California Department of Public Health (CDPH), and the US Census.
Prepared by:
Emanuel Alcala, MA
John Capitman, PhD
Suggested Citation:
Central Valley Health Policy Institute (2017). Adolescent Health in the San Joaquin Valley: Individual and Neighborhood Characteristics. California State University, Fresno.
Copyright Information
Copyright © 2017 by California State University, Fresno. This report may be printed and distributed free of charge for academic or planning purposes without the written permission of the copyright holder. Citation as to source, however, is appreciated. Distribution for profit of this material is prohibited without specific permission of the copyright holder.
Executive Summary
Context
Promoting healthy and appropriately timed pregnancies and births are key objectives for public health. While substantial achievements have been made, the United States is now behind many peer high-income nations in achieving key World Health Organization maternal and child health. This reflects great variability in outcomes across the US and California. An evidence-based consensus has emerged that both modifiable individual factors and modifiable neighborhood exposures dramatically impact reproductive health outcomes. This report examines reproductive health outcomes and determinants in the San Joaquin Valley (SJV), focusing on teen births and birth outcomes.
Teen Child-Bearing
Because pregnancy and child-bearing by teenagers is associated with long term negative social, economic and health outcomes for the teen mother, her child and the larger society, reductions in teen pregnancy and births has been a major focus of public health initiatives. By 2014 the teen birth rate was about 24 births/1,000 adolescent females, almost 1/3 of the 1990 rate. California teen child-bearing varies by race/ethnicity, social class, and place of residence. The recent California legal mandates to provide comprehensive reproductive health education and confidential access to health care have broadened access to effective programs, but many also face barriers to accessing care.
Birth Outcomes: Preterm Birth
For newborns, there are multiple measures of well-being that are complexly correlated. Adverse birth outcomes include low birth weight (LBW), preterm birth (PTB), infant morbidity (failure to thrive and other diagnosed medical conditions) and infant mortality (birth - one year). Recent studies have pointed to PTB as the most consistent indicator of poor maternal and infant health. PTB is associated with other poor infant health outcomes and long-term economic and social challenges for individuals and communities. PTB has been attributed to maternal age, chronic health conditions, and high risk behaviors. According to March of Dimes data, women who become pregnant in the SJV face a much higher risk of PTB compared to other regions within the state, particularly women of color and those who reside in low-income communities.
A common set of individual and neighborhood factors have been linked to adverse maternal and child health outcomes such as PTB. Many of these same factors have been linked to teenage pregnancy and child-bearing. Women with individual risk factors such as poverty, low education, challenging work, and racial/ethnic “minority” status face greater stresses before and during pregnancy, have less access to preventive care and pregnancy care, and have more adverse birth outcomes. Similarly, living in poor, segregated, conflict-filled and polluted neighborhoods seems to increase risk for adverse birth outcomes beyond the effect of individual factors. These stark differences are explored in research utilizing the life course perspective, a combination of early programming, and cumulative pathway theories.
Current San Joaquin Valley Public Health Consortium Programs Supporting the Health of Young Women
San Joaquin Valley Public Health Consortium (SJVPHC) member local health departments have extensive programming centered on women and children. The success of these initiatives hinge on state and federal policies and funding priorities. Notable reductions in funding for public health maternal and child health initiatives in California have also influenced the range and scope of interventions supporting this vulnerable population. Despite these factors, Table 1 shows diverse examples from the SJV county local health departments of ongoing initiatives and activities to promote the health of young women. By examining variations across the SJV, this analysis can help local health departments and their partners identify additional avenues to improve the health of young women.
| County | Examples of Current Initiatives |
|---|---|
| Kings |
|
| Fresno |
|
| Madera |
|
| Merced |
|
| San Joaquin |
|
| Stanislaus |
|
| Tulare |
|
Data Sources and Approach
This report utilizes data from a variety of statewide governmental agencies. Hospital discharge data and the birth statistical master files for the years 2009-2013 were obtained from the Office of Statewide Health Planning and Development (OSHPD) and the California Department of Public Health (CDPH), respectively. The Office of Environmental Health Hazard Assessment (OEHHA) identified and grouped key indicators to produce the CalEnviroScreen (CES) score. Pollution burden and population characteristics are the two indices that create the cumulative impact score from the CES 2.0. Indicators that compose the pollution burden score, including particulate matter 2.5 (PM2.5) and diesel particulate matter, were used to highlight neighborhood level influences on women’s health. The Regional Opportunity Index (ROI) is an index that helps to target resources and economic opportunity in California’s communities developed by UC Davis Center of Regional Change. All data files mentioned above provided information on place of residence (zip code or census tract), age, sex, and other non-identifiable demographics. All rates and population estimates were based on 2010 Census files.
Findings: Teen Births
The SJV counties has some of the highest rates of teen birth observed in the state of California, but they have seen dramatic reductions in teen birthing in recent years. Figure 1 illustrates that all eight counties of the SJV have significantly higher rates of teen births than the state as a whole. The Figure also demonstrates a clear downward trend over time for California and the SJV Counties. An 11% decrease in teen births was observed for California over the five year period, while a similar trend was observed for each of the the SJV counties. In addition to having higher rates of teen births than other parts of the State, the rates also vary notably by residence in the Valley as shown in Figure 2.
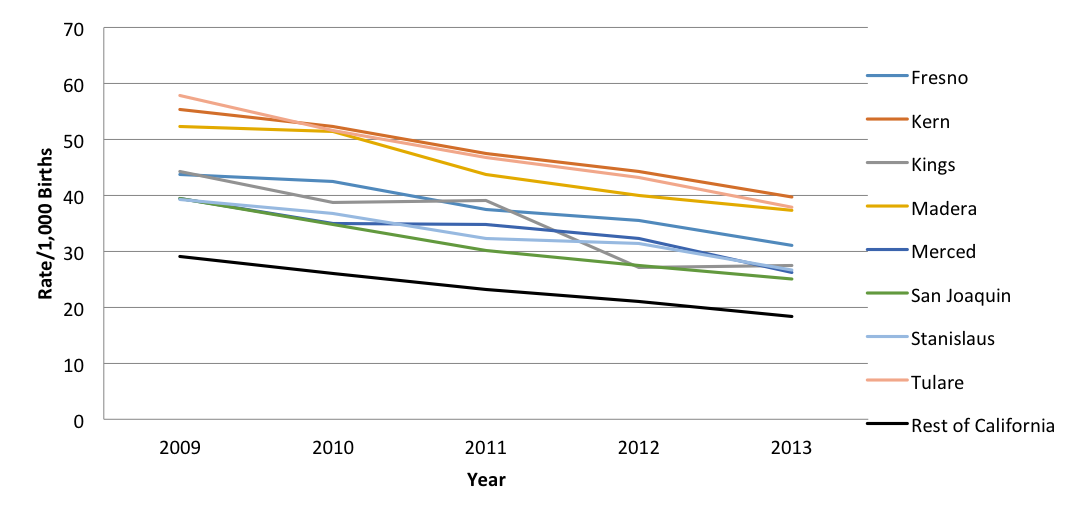
Chart description: Nine lines show rates for Fresno, Kern, Kings, Madera, Merced, San Joaquin, Stanislaus, Tulare, and the Rest of California for 2009, 2010, 2011, 2012, and 2013. The vertical axis is labeled Rate/1,000 Births and ranges from 0 to 70 in increments of 10. Rates decline over the period in all nine series, and each San Joaquin Valley county remains above the Rest of California. Individual data points are not numerically labeled.

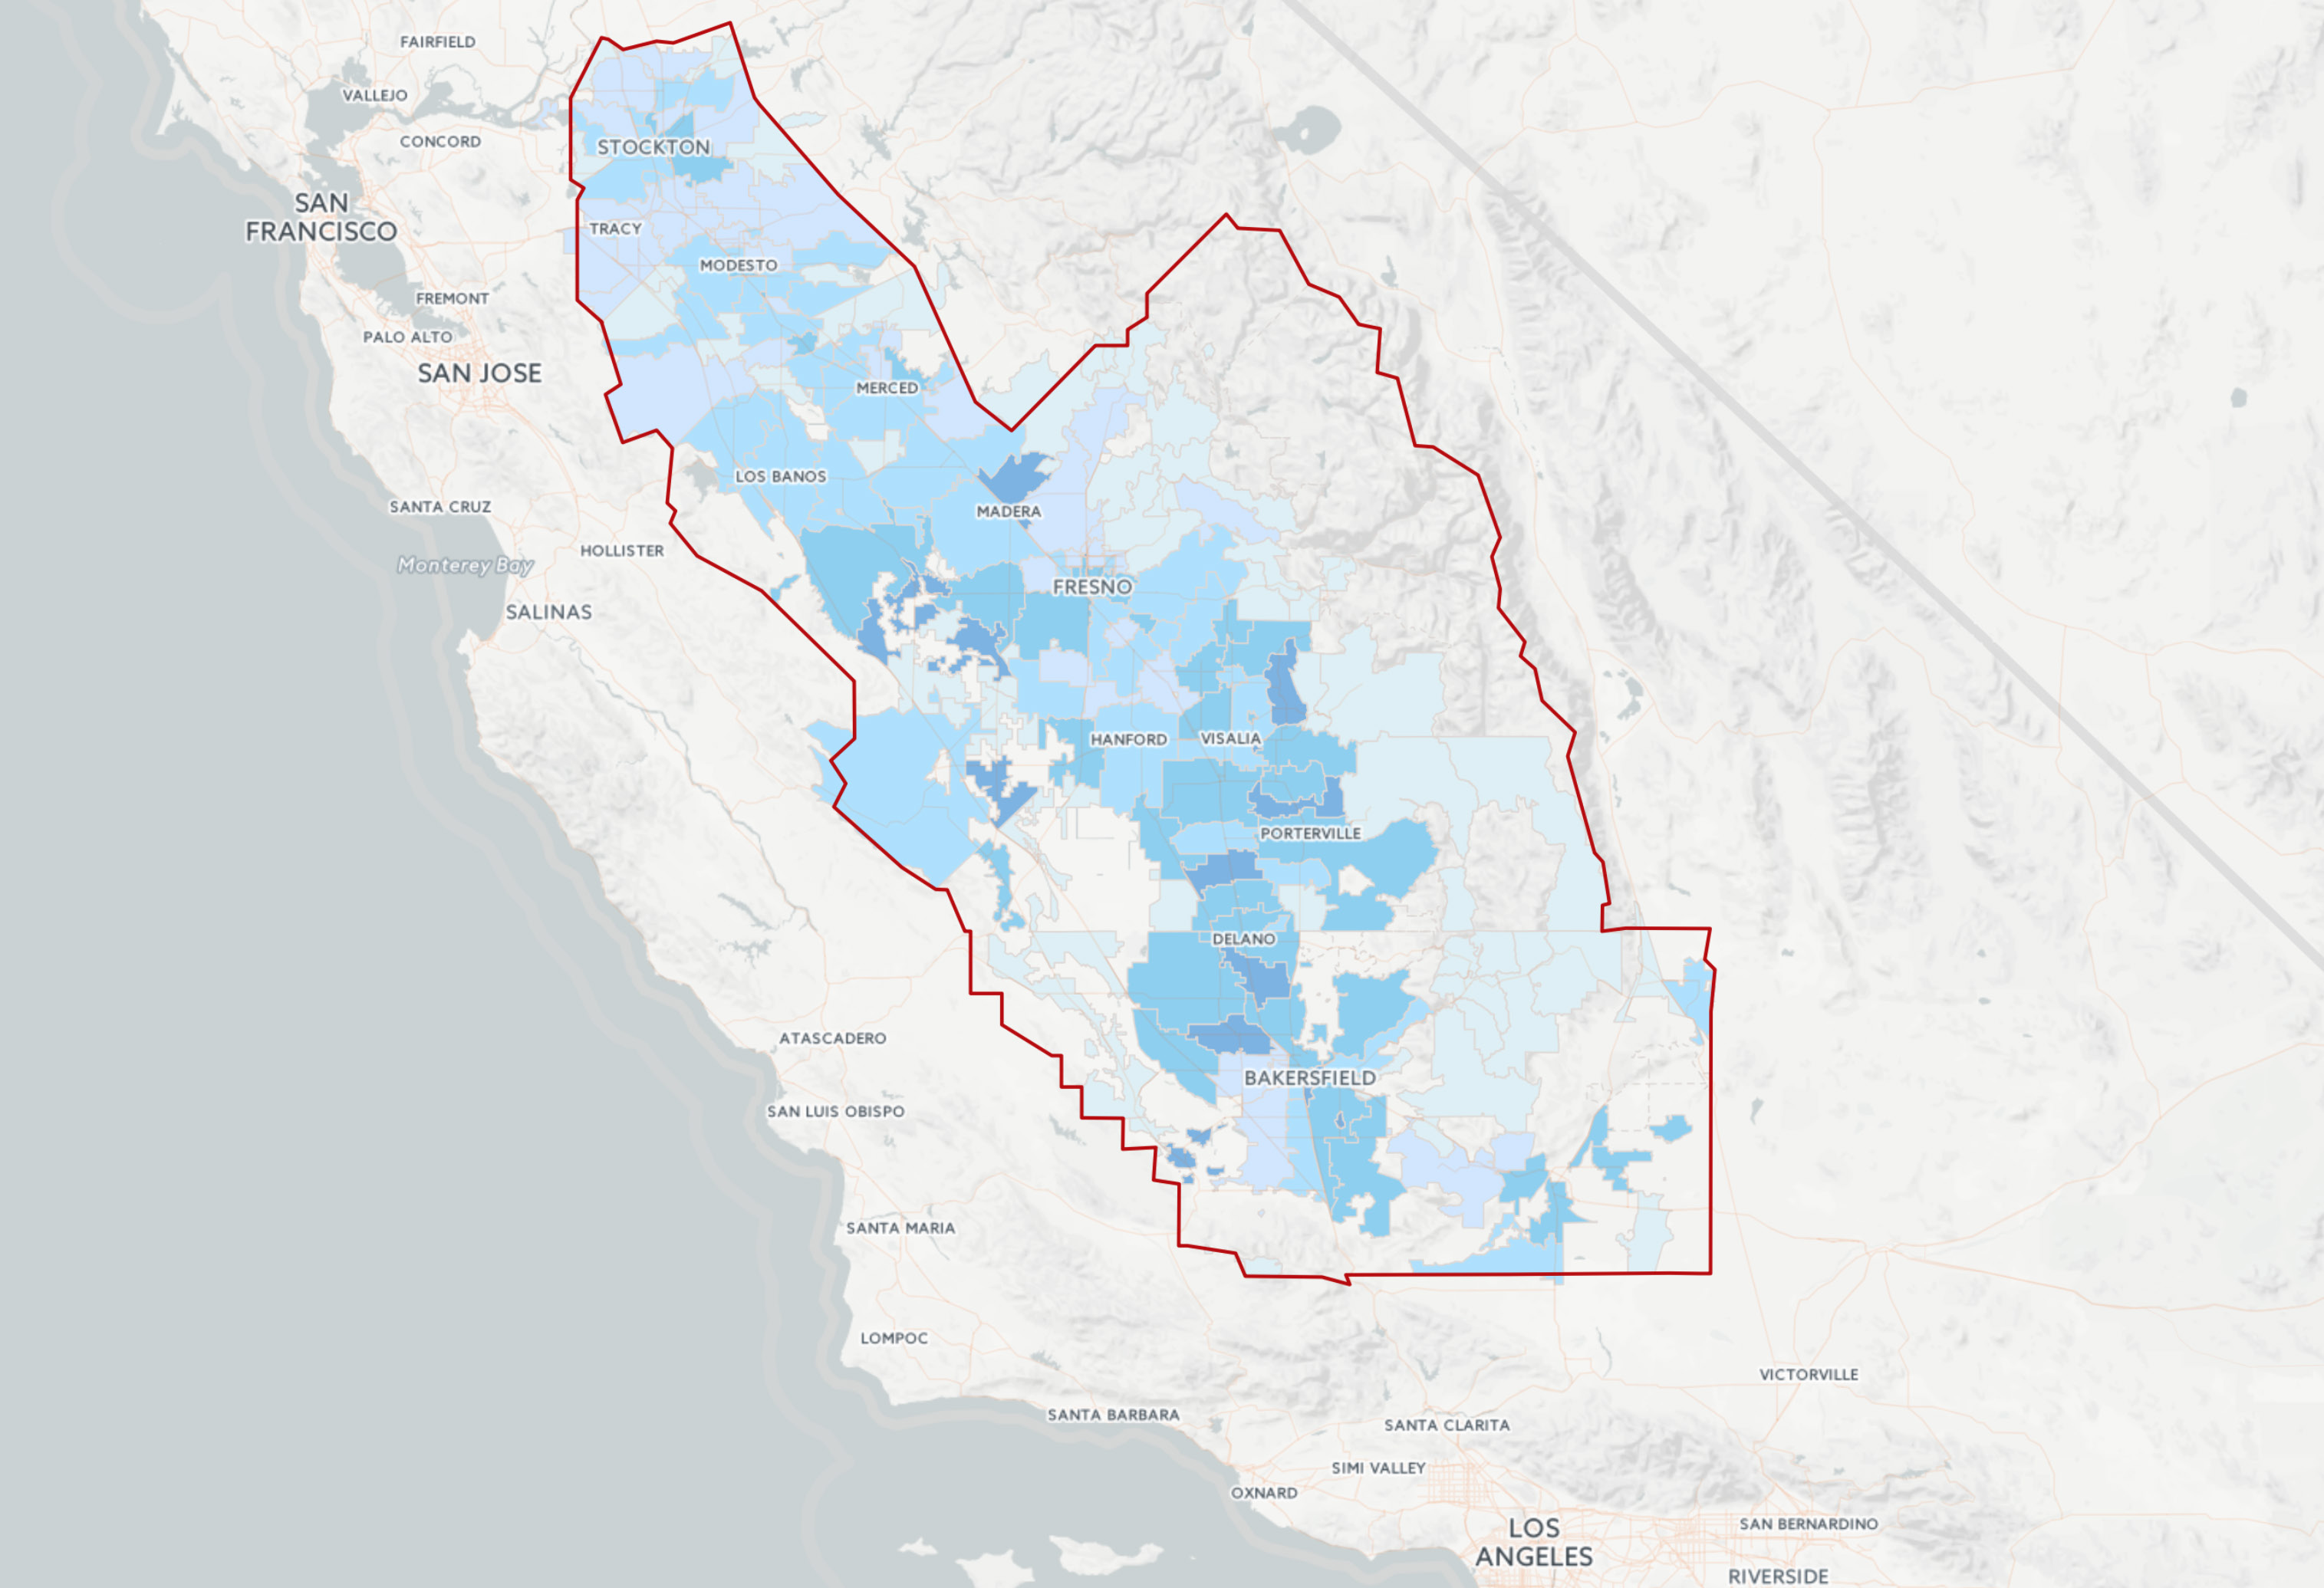
Map description: ZIP codes are shaded within the San Joaquin Valley, extending from the Stockton area in the north to the Bakersfield area in the south. The legend is labeled Teen Birth Rate 2010 to 2012 and ranges from 0 to 89. Lighter blue indicates lower rates and darker blue indicates higher rates.
Our analysis suggests, teen pregnancy varies by individual level indicators as well as across communities in the SJV. We examined the odds ratios and 95% confidence intervals in multivariate analysis. Women of color are at significantly higher risk for teen births, when compared to white women. Specifically, Latinas, African-Americans, Asians, and “Other” were at 2.28, 1.63, 2.10, and 2.10 times more likely for teen births than Whites, respectively. Foreign-born women were found to be 0.45 times less likely to have a teen birth than US-born women. Mothers on Medi-Cal and other public insurance types are 4.57 and 2.87 times more likely to have a teen birth than mothers with private coverage, respectively. Neighborhood poverty is positively associated with teen birth rates. In communities where at least 18% of the population was living two times below the Federal Poverty Level, the odds for teen birth were 1.38 times greater than in affluent communities. In communities considered to be in extreme poverty, where at least 33% of individuals were living two times below the Federal Poverty Level, the odds for teen birth were 1.46 times greater than in affluent communities.
| Indicator or group | Comparison group | Odds ratio |
|---|---|---|
| Latinas | White women | 2.28 |
| African-Americans | White women | 1.63 |
| Asians | White women | 2.10 |
| “Other” race/ethnicity | White women | 2.10 |
| Foreign-born women | US-born women | 0.45 |
| Mothers on Medi-Cal | Mothers with private coverage | 4.57 |
| Mothers on other public insurance | Mothers with private coverage | 2.87 |
| Communities where at least 18% of the population was living two times below the Federal Poverty Level | Affluent communities | 1.38 |
| Communities where at least 33% of individuals were living two times below the Federal Poverty Level | Affluent communities | 1.46 |
Preterm Birth
During the study period, the proportion of PTBs was greater within the SJV region, 9.4%, than the state, 8.8%. Overall, the SJV has higher rates of premature birth than the state. There was considerable variation by residence and other factors within the SJV, as well. Figure 3 displays individual and neighborhood level indicators significantly associated with preterm birth (PTB), as determined by a hierarchical regression model. Odds ratios and 95% confidence intervals are displayed in order to show the magnitude of the relationship between each indicator and PTB. Indicators are categorized into two groups, modifiable and non-modifiable.
Mothers who were older than 29 years of age were found to be at significantly higher risk for PTB, in comparison to mothers between the age of 25 and 29. Mothers between the age of 20 and 24 were significantly less likely for PTB. African-Americans were at significantly greater risk than Whites, with an OR of 1.58. Asians and “other” races/ethnicities were also at significantly greater risk than Whites, with 1.33 and 1.28 odds ratio, respectively. Modifiable indicators were found to have a greater association with PTB when compared to non-modifiable. Having a previous PTB, hypertension, or smoking increased risk for PTB. Mothers on Medi-Cal and other forms of public insurance were at 1.21 and 1.33 times more likely to have a PTB than mothers who had private insurance. Although individual-level indicators explained for the majority of variation in PTB, particulate matter 2.5 (PM2.5) and economic opportunity measured at the zip code level were significantly associated with PTB even after controlling for individual level differences. PM2.5 was significant and positively associated with PTB. The indicator for poverty—economic opportunity—was significant and negatively associated with PTB. This suggested that in communities where economic opportunity was highest, the lowest rates of PTB were observed.
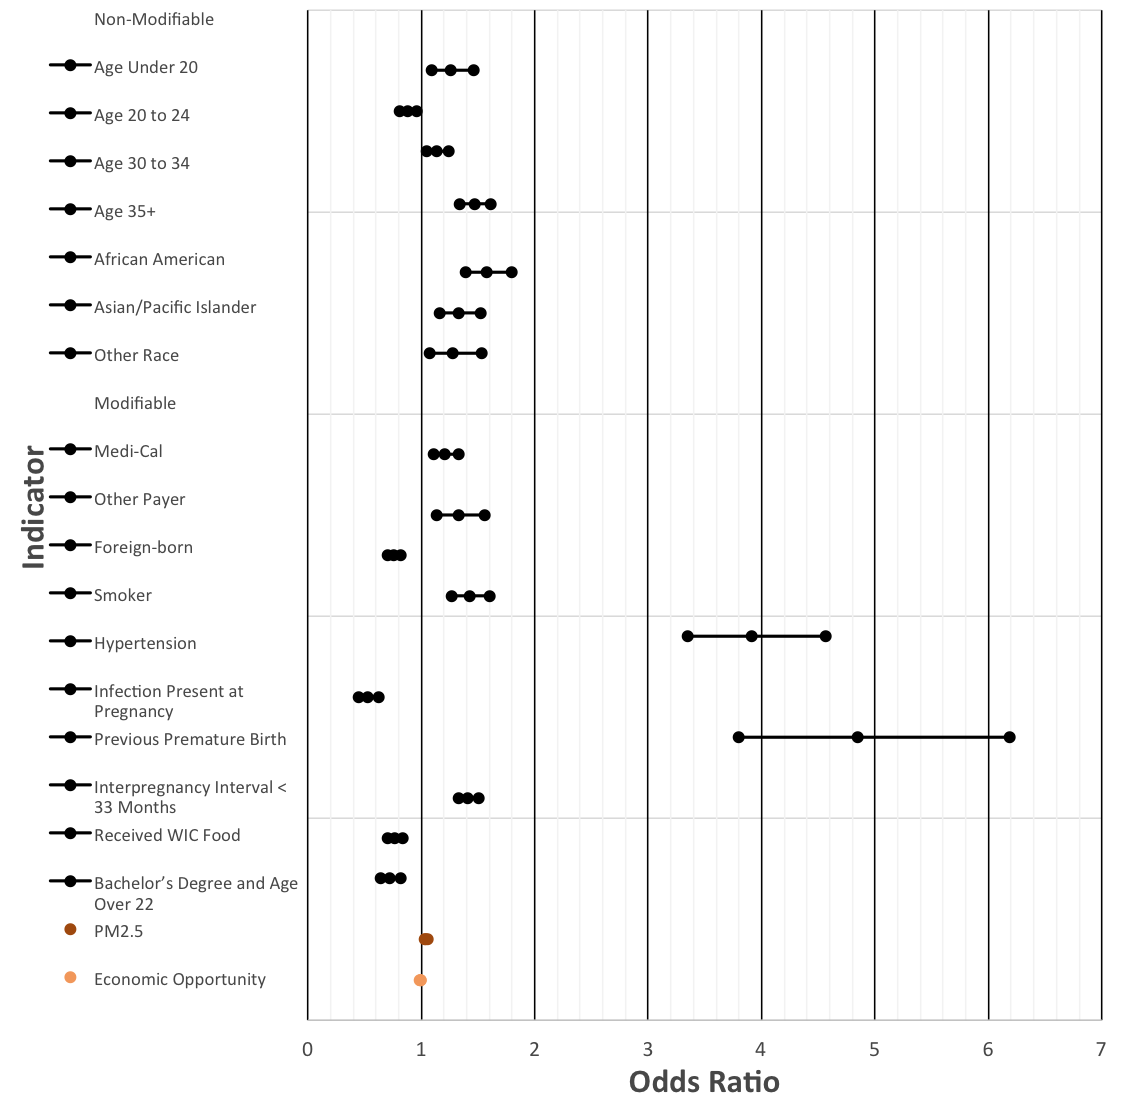
Chart description: Points and horizontal lines show odds ratios and 95% confidence intervals. The horizontal Odds Ratio axis ranges from 0 to 7, with 1 marking equal odds. Black points represent individual indicators; colored points represent the neighborhood indicators PM2.5 and Economic Opportunity. Numerical values are not printed beside the plotted points or interval endpoints.
| Indicator | Association shown in the chart | Odds ratio stated in text |
|---|---|---|
| Non-Modifiable | ||
| Age Under 20 | Greater odds | — |
| Age 20 to 24 | Lower odds | — |
| Age 30 to 34 | Greater odds | — |
| Age 35+ | Greater odds | — |
| African American | Greater odds | 1.58 |
| Asian/Pacific Islander | Greater odds | 1.33 |
| Other Race | Greater odds | 1.28 |
| Modifiable: individual indicators | ||
| Medi-Cal | Greater odds | 1.21 |
| Other Payer | Greater odds | 1.33 |
| Foreign-born | Lower odds | — |
| Smoker | Greater odds | — |
| Hypertension | Greater odds | — |
| Infection Present at Pregnancy | Lower odds | — |
| Previous Premature Birth | Greater odds | — |
| Interpregnancy Interval < 33 Months | Greater odds | — |
| Received WIC Food | Lower odds | — |
| Bachelor’s Degree and Age Over 22 | Lower odds | — |
| Neighborhood indicators | ||
| PM2.5 | Greater odds | — |
| Economic Opportunity | Lower odds | — |
Greater or lower odds indicates whether the plotted odds ratio is above or below 1. The numerical odds ratios in the table are those stated in the report’s accompanying text. A dash means that the text does not state an exact odds ratio for that indicator.
Discussion and Recommendations
Although rates of teen birthing are elevated in the SJV relative to California, the 2009-2013 period saw continued year-to-year reductions in these rates throughout the region. Teen birthing varied by individual and neighborhood factors, with individual and neighborhood poverty as the strongest predictors. Despite notably high rates of pregnancy care engagement, the SJV has higher rates of adverse birth outcomes than California as a whole. A number of the individual and neighborhood factors associated with PTB rates explain elevated risk compared to other CA region and variability within the region. Women of color with low education and prior PTBs as well as those in communities with high diesel pollution and low economic opportunity were at greatest risk for PTB.
The local health departments have taken varied strategies to promote reproductive health in order to have maximum impact on communities. Generally, these strategies have targeted modifiable characteristics of individuals. The San Joaquin Valley local health departments have a long history of providing free STI/HIV testing as well as in reducing tobacco marketing. The findings within this report suggest that the San Joaquin Valley continues to host reproductive disparities which are pervasive among women who are of color, low education status, low socioeconomic status, and young.
Potential Initiatives to Reproductive Health
The SJV Public Health Consortium identified three specific opportunities that county public health departments can champion at the county level:
- Promote high quality and culturally responsive reproductive clinical care in patient-centered systems, informed by scientific consensus and national best practice evidence. In the SJV, several counties are fostering opportunities to train and retain physicians, advanced practice nurse and other practitioners that are multi-lingual and culturally sensitive. They are developing new partnerships to increase access to quality, coordinated and evidence-based care.
- Provide individually oriented education, health promotion, screening and interventions for women of reproductive age to reduce risk factors for adverse outcomes. The “promotora” or community health worker (CHW) model is being implemented to provide social, economic and health support for women. CHWs visit women in home settings to promote preventive measures including breastfeeding, nutrition, homemaker assistance, healthcare system navigation, etc. Developing sustainable funding for these programs is a high priority goal for several SJV counties.
- Investigate and increase the responsiveness of policies and programs to social, economic and environmental factors that impact pregnancy and early childhood outcomes. This multi-level, interdisciplinary goal requires new collaborations and unique partnerships. Some counties in the SJV are coordinating across sectors to consider the built environment and adopt health-friendly policies and improve the physical infrastructure for healthy living. Those invited to engage and frame new policies include government agencies, businesses, employers, developers, and families.